Numerous diseases can cause congestive heart failure (CHF).
Common causes of left-sided congestive heart failure in adults are ischemic heart disease, arrhythmia, and vulvlar diseases. In addition to these common causes, there are other rare causes of left-sided congestive heart failure.
There are a few reports of left ventricular (LV) dysfunction caused by isolated adrenocorticotrophic hormone (ACTH) deficiency.
Adrenal Insufficiency - Primary, Secondary, or Tertiary
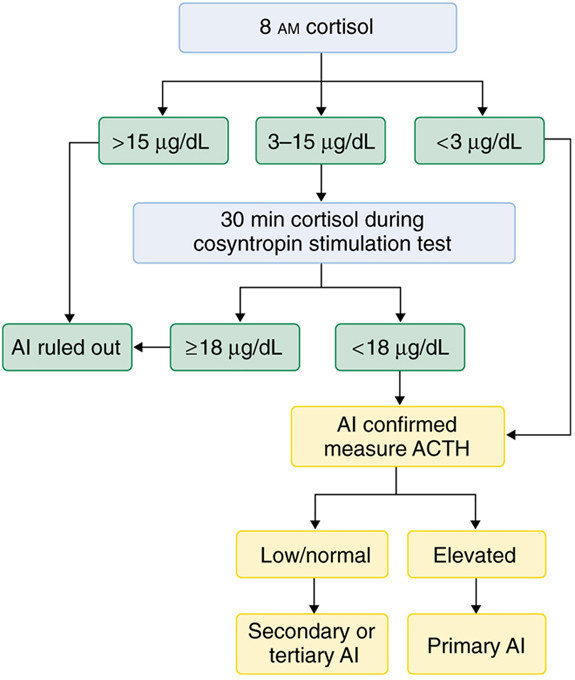
The onset of adrenal insufficiency is often very gradual, and it may go undetected until an illness or other stress precipitates adrenal crisis.
Adrenal insufficiency can be primary, secondary, or tertiary. The hallmark laboratory finding is an inappropriately low ACTH value in the setting of diminished cortisol concentrations.
Adrenal insufficiency can be caused by diseases of the adrenal gland (primary), interference with corticotropin (ACTH) secretion by the pituitary gland (secondary), or interference with corticotropin-releasing hormone (CRH) secretion by the hypothalamus (tertiary). The hallmark laboratory finding is an inappropriately low ACTH value and/or diminished cortisol concentrations.
Primary adrenal insufficiency (Addison's disease) is due to adrenocortical disease, while secondary and tertiary adrenal insufficiency are due to disorders of the pituitary gland (corticotropin [ACTH] secretion) or the hypothalamus (corticotropic-releasing hormone secretion), respectively.
Primary adrenal insufficiency is associated with both cortisol and mineralocorticoid deficiency.
Where as, secondary and tertiary adrenal insufficiency are associated with cortisol, but not mineralocorticoid deficiency, because aldosterone is regulated primarily by the renin-angiotensin system, which is independent of the hypothalamus and pituitary. This distinction accounts for the different clinical presentation and management of these disorders.
The renin-angiotensin-aldosterone system is a series of reactions designed to help regulate blood pressure. is a hormone system that regulates blood pressure, fluid and electrolyte balance, as well as systemic vascular resistance.
Clinical manifestations of primary adrenal insufficiency include fatigue, hypotension, hyponatremia (sodium levels in the blood are lower than normal), hyperkalemia (high potassium blood levels), hypoglycaemia (low blood sugaars), and hyperpigmentation of the skin.
Clinical features of secondary adrenal insufficiency don't have hypotension, hyperkalemia, and hyperpigmentation due to normal function of the renin-angiotensin-aldosterone system (RAAS) and low levels of ACTH.
Hypoglycemia can occur more often in patients with central hypoadrenalism since growth-hormone deficiency may also be present.
Secondary Adrenel Insufficiency
Any process that involves the pituitary and interferes with corticotropin (ACTH) secretion can cause secondary adrenal insufficiency. The ACTH deficiency may be isolated or occur in conjunction with other pituitary hormone deficiencies (panhypopituitarism).
Panhypopituitarism - Any disease that affects the pituitary gland can result in diminished secretion of one or more pituitary hormones. Pituitary tissue can be destroyed and hormone secretion reduced by large pituitary tumors or craniopharyngiomas, infectious diseases such as tuberculosis or histoplasmosis, infiltrative diseases, lymphocytic hypophysitis, head trauma, and large intracranial artery aneurysms.
Pituitary infarction can occur at the time of delivery if excessive blood is lost and hypotension occurs (Sheehan syndrome), and hemorrhage may occur into a pituitary tumor (pituitary apoplexy). Pituitary metastases are sometimes (approximately 5 percent) found in patients with disseminated cancer at autopsy; however, these metastases rarely reduce hormone secretion [2].
Adrenel Crisis
Main features - The predominant manifestation of adrenal crisis is shock, but the patients often have nonspecific symptoms such as anorexia, nausea, vomiting, abdominal pain, weakness, fatigue, lethargy, fever, confusion, or coma.
In one study, the incidence of adrenal crisis was similar in patients with primary (8 percent) and secondary (6 percent) causes of adrenal insufficiency [3].
Major factors— As suggested by its occurrence in both causes of adrenal insufficiency, both mineralocorticoid and glucocorticoid deficiency can participate in the development of adrenal crisis.
The physiologic basis for this is the ability of aldosterone or synthetic mineralocorticoid to promote sodium retention as well as to enhance vasoconstrictor responses of the vasculature [4].
Adrenal crisis can occur in patients who are receiving physiologic or even pharmacologic doses of synthetic glucocorticoid if their mineralocorticoid requirements are not met [3,4].
Glucocorticoid deficiency can contribute to hypotension by causing decreased vascular responsiveness to angiotensin II and norepinephrine, decreased synthesis of renin substrate, and increased prostacyclin production [5-7].
There is almost always an acute stressor or cause of adrenal insufficiency in patients with adrenal crisis.
Adrenel Insufficiency and Cardiovascular Risk
Recent studies have shown an association between adrenal insufficiency (AI) and increased cardiovascular risk (CVR).
Patients with AI receive glucocorticoid (GC) replacement therapy which can lead to varying levels of blood cortisol.
Studies have shown that imbalances in blood cortisol may lead to a higher prevalence of coronary heart disease, major adverse coronary events, and increased mortality.
Glucocorticoid substitution is essential in the treatment of adrenal insufficiency without which the disease has been shown to be fatal.
The most frequently used glucocorticoid formula for replacement therapy is hydrocortisone (HC) or prednisolone.
Overreplacement of glucocorticoid may lead to adverse effects including obesity, high blood pressure, and hyperglycaemia.
The outcome may vary between primary and secondary adrenal insufficiency mainly due to differences in the renin-angiotensin-aldosterone system (RAAS).
Physicians and patients should be properly educated about the increased risk of CVD in patients with adrenal insufficiency from either primary (Addison disease) or secondary adrenal insufficiency.
Primary adrenal insufficiency (AI) is a rare disease with a prevalence of approximately 100 to 126 cases per million in the western world.
The leading cause of primary adrenal insufficiency is autoimmune disease, tuberculosis associated adrenalitis remains an important cause in developing countries.
Certain drugs such as mitotane, ketoconazole, metyrapone, and etomidate may lead to primary adrenal insufficiency due to their inhibiting effect on adrenal enzymes.
ACTH-deficiency in the pituitary gland results in secondary adrenal insufficiency with an estimated prevalence of 45.5 per 100,000.
Both types of adrenal insufficiency lead to a lack of natural or endogenous glucocorticoids (GC), while absence of mineralocorticoids is limited to primary adrenal insufficiency.
Glucocorticoid replacement is necessary in both primary and secondary adrenal insufficiency to prevent harmful symptoms or even death.
Glucocorticoid replacement meds try to mimic the physiological rhythm of natural or endogenous cortisol as accurately as possible.
However, temporary supra- and subphysiological levels of blood cortisol are common and may be harmful.
In fact, patients with adrenal insufficiency on glucocorticoid replacement therapy appear to have an increased overall mortality.
Recently, some studies have shown that this is mainly due to an increased cardiovascular risk (CVR) owing to the glucocorticoid replacement therapy itself.
A dose of hydrocortisone exceeding 20 mg per day seems to be associated with increased cardiovascular risk due to the higher prevalence of common metabolic risk factors (obesity, high blood sugars).
It is conceivable that glucocorticoid therapy affects some of the well-known risk factors for cardiovascular disease (CVD), for example, obesity, hypertension, diabetes, and hyperlipoproteinemia (elevated cholesterol).
This can be observed in patients with Cushing's disease suffering from these symptoms due to an ACTH-producing tumor in the pituitary gland or a cortisol secreting tumor in the adrenal gland.
Exogenous (supplement medicine0 glucocorticoid therapy may result in similar clinical manifestations that are also described as iatrogenic Cushing's disease.
The ideal amount of glucocorticoid substitution in adrenal insufficiency patients remains at debate, especially when balancing advantages and adverse effects of the therapy.
In a population based case-control study with 50,656 patients having received at least one prescription for systemic or nonsystemic glucocorticoids, Souverein et al. showed an increased risk for cardiovascular and cerebrovascular events when compared to matching controls without GC intake with an adjusted odds-ratio of 1.25 (95% confidence interval (CI) 1.21 to 1.29)
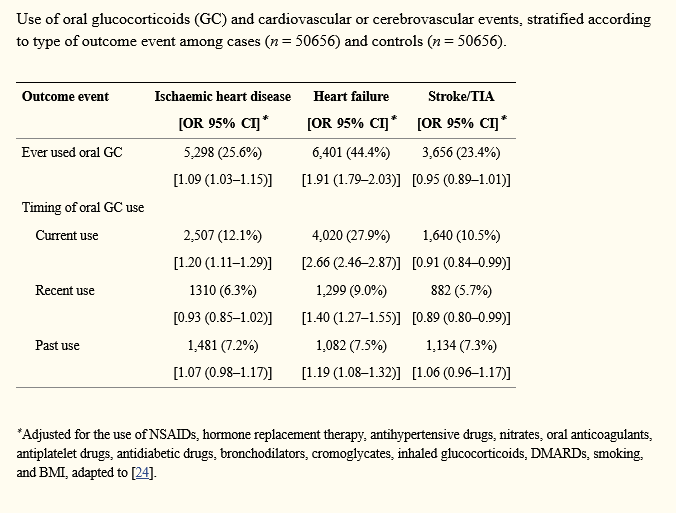
Source: see reference 8
Of interest, higher levels of low-density lipoprotein (LDL) were identified in patients receiving prednisolone instead of hydrocortisone while HbA1c, high-density lipoprotein and triglyceride levels, body mass index, systolic and diastolic blood pressure, and waist circumference showed no significant difference.
Patients suffering from hormone-inactive tumors of the pituitary receiving hydrocortisone replacement therapy seem to have an increased risk of developing diseases such as hypertension, diabetes, hyperlipoproteinaemia, coronary heart disease, or atrial fibrillation when compared to those with normal hormone function or hormone producing adenomas of the pituitary gland.
pBNP Is Not A Clear Indicator for Congestive Heart Failure (CHF with Adrenal Insufficancy Patients or Renal Patients
Congestive heart failure (CHF) is a complex syndrome characterized by sodium and water retention through the activation of different neurohormonal systems, such as the renin-angiotensin-aldosterone system RAAS and the sympathetic nervous system (SNS), and also importantly, the NP system.
pBNP levels are relatively higher in patients with chronic kidney disease and no heart disease, the mechanism remains unknown.
BNP is protective against chronic kidney diseases and heart failure, especially in terms of the counterparts of the renin-angiotensin-aldosterone system (RAAS).
The renoprotective effects of BNP include the inhibition of sodium reabsorption in the proximal tubule and the distal nephron, and the improvement of the glomerular filtration rate (GFR) and renal plasma flow (RPF) with respect to vasodilatation by inhibiting multiple plasma vasoconstrictors.
Hyponatremia (low blood sodium levels) is often seen in patients with adrenal insufficiency, which is caused by an inappropriate increase in vasopressin secretion/action due to cortisol deficiency and the inability to excrete free water.
With adrenal insufficancy, kidneys are stresses as sodium levels are reduced, as a result, deterioration in kidney function increased BNP and NT-proBNP levels, as well as the NT-proBNP/BNP ratio.
Although circulating levels of both BNP and NT-proBNP increased with deteriorating kidney function, the impact of kidney function on NT-proBNP was much more pronounced than that on BNP. Kidney function should be taken into account when interpreting data on BNP, NT-proBNP and their relationship.
Cardioloigists need to be careful assuming that an elevation in pBNP or BNP is from CHF exclusively, Adrenol insufficiency can be the underlying cause.
Need for Patient Education
With adrenal insufficiency the cardiovascular risk in patients with shows that there is a strong need for patient education not only the underlying disease itself but also a risk reduction of known factors such as obesity, high blood pressure, diabetes mellitus, and hyperlipidaemia.
Patients need to be informed about the increased risk for cardiovascular events and the need for regular check-ups, by both an endocrinologist and a cardiologist.
Physicians in general but especially cardiologists should be educated about the higher incidence of cardiovascular events in adrenal insufficiency patients and recognize clinical manifestations of adrenal insufficiency that may vary strongly between patients.
Glucocorticoids replacement therapy in adrenal insufficiency has not changed significantly in the past decades.
The goal of current replacement therapy is to try to mimic the physiological secretion of cortisol as accurately as possible, there is still a lot of room for improvement.
Similar to insulin therapy in diabetes, glucocorticoids replacement therapy should focus on avoiding serious side effects while guaranteeing an adequate substitution of the deficient hormone.
Today, newer synthetic cortisol formulas offer a delayed-release delivery system that offer better therapeutic options.
Studies show increased quality of life and improvement in metabolic profile using dual-release hydrocortisone preparations such as Plenadren. The slow-releasing mechanism of these new glucocorticoid substitution formulas may also avoid temporary subphysiological levels of cortisol.
References:
1. Grossman AB. Clinical Review#: The diagnosis and management of central hypoadrenalism. J Clin Endocrinol Metab 2010; 95:4855.
2. Modhi G, Bauman W, Nicolis G. Adrenal failure associated with hypothalamic and adrenal metastases: A case report and review of the literature. Cancer 1981; 47:2098.
3. Hahner S, Loeffler M, Bleicken B, et al. Epidemiology of adrenal crisis in chronic adrenal insufficiency: the need for new prevention strategies. Eur J Endocrinol 2010; 162:597.
4. Feldman RD, Gros R. Vascular effects of aldosterone: sorting out the receptors and the ligands. Clin Exp Pharmacol Physiol 2013; 40:916.
5. Saruta T, Suzuki H, Handa M, et al. Multiple factors contribute to the pathogenesis of hypertension in Cushing's syndrome. J Clin Endocrinol Metab 1986; 62:275.
6. Ohtani R, Yayama K, Takano M, et al. Stimulation of angiotensinogen production in primary cultures of rat hepatocytes by glucocorticoid, cyclic adenosine 3',5'-monophosphate, and interleukin-6. Endocrinology 1992; 130:1331.
7. Jeremy JY, Dandona P. Inhibition by hydrocortisone of prostacyclin synthesis by rat aorta and its reversal with RU486. Endocrinology 1986; 119:661.
8. Souverein P. C., Berard A., Van Staa T. P., et al. Use of oral glucocorticoids and risk of cardiovascular and cerebrovascular disease in a population based case-control study. Heart. 2004;90(8):859–865. doi: 10.1136/hrt.2003.020180